
AI · Healthcare
HL7 vs FHIR: Understanding Healthcare Data Interoperability Standards for AI Integration
Understand the difference between HL7 and FHIR in 2026, why FHIR R4 is the foundation for healthcare AI integration, and how to build a modern interoperability architecture.
Secure Traces Healthcare and Pharmacy Technology practice works directly with healthcare technology leaders navigating HL7 and FHIR integration decisions, providing security architecture guidance that keeps interoperability investments aligned with HIPAA requirements and clinical risk management priorities. Secure Traces AI Solutions practice helps healthcare organizations evaluate FHIR R4 data architectures for AI integration, including vector store design, PHI guardrails, and MCP gateway governance that enables governed agentic access to live FHIR data.
across hundreds of different vendor platforms, making it extraordinarily difficult to assemble a complete, accurate picture of a patient's clinical history at the point of care.
The consequences of this fragmentation are clinical, operational, and financial. Clinicians make decisions without complete information. Care coordination between providers breaks down at transitions of care. Revenue cycle teams spend enormous resources reconciling data discrepancies between clinical and billing systems. And the AI systems that healthcare organizations are now deploying to improve care quality and operational efficiency cannot function effectively if the data they need to process is locked in siloed, non-interoperable formats.
HL7 and FHIR are the two dominant healthcare data interchange standards that govern how clinical information is structured and exchanged between systems. Understanding what each standard is, how they differ, where each is most appropriate, and how they relate to AI integration is essential knowledge for any healthcare technology leader making integration architecture decisions in 2026.
This article explains both standards in practical terms, compares them across the dimensions that matter most for integration architecture decisions, and explains why FHIR R4 has become the foundational standard for healthcare AI integration.
What Is HL7?
Health Level Seven, universally known as HL7, is a set of international standards for the exchange, integration, sharing, and retrieval of electronic health information. The organization that maintains these standards, Health Level Seven International, has been developing and publishing healthcare data exchange standards since 1987.
The term HL7 most commonly refers to HL7 version 2, which is the messaging standard that became the dominant clinical data exchange format across the United States and much of the world over the past three decades. HL7 v2 messages are the mechanism through which most EHR systems today communicate laboratory results, admission and discharge notifications, order messages, pharmacy transactions, and scheduling information.
Understanding HL7 v2 Messages
An HL7 v2 message is a structured text string composed of segments, fields, components, and subcomponents separated by defined delimiter characters. Each message type has a defined structure that specifies what data elements appear in which positions within the message.
For example, an ADT message, which stands for Admit Discharge Transfer, notifies receiving systems of patient registration events. An ORU message, which stands for Observation Result Unsolicited, carries laboratory and other clinical observation results from producing systems to consuming systems. An ORM message, which stands for Order Message, carries clinical orders from ordering systems to receiving departments.
The power of HL7 v2 was its early adoption and the enormous ecosystem of integration engines and system interfaces built around it over thirty-plus years. Virtually every clinical system in use in US healthcare today can send or receive HL7 v2 messages, making it the lingua franca of clinical system integration.
The Limitations of HL7 v2
HL7 v2 carries significant limitations that have become increasingly problematic as healthcare technology has evolved.
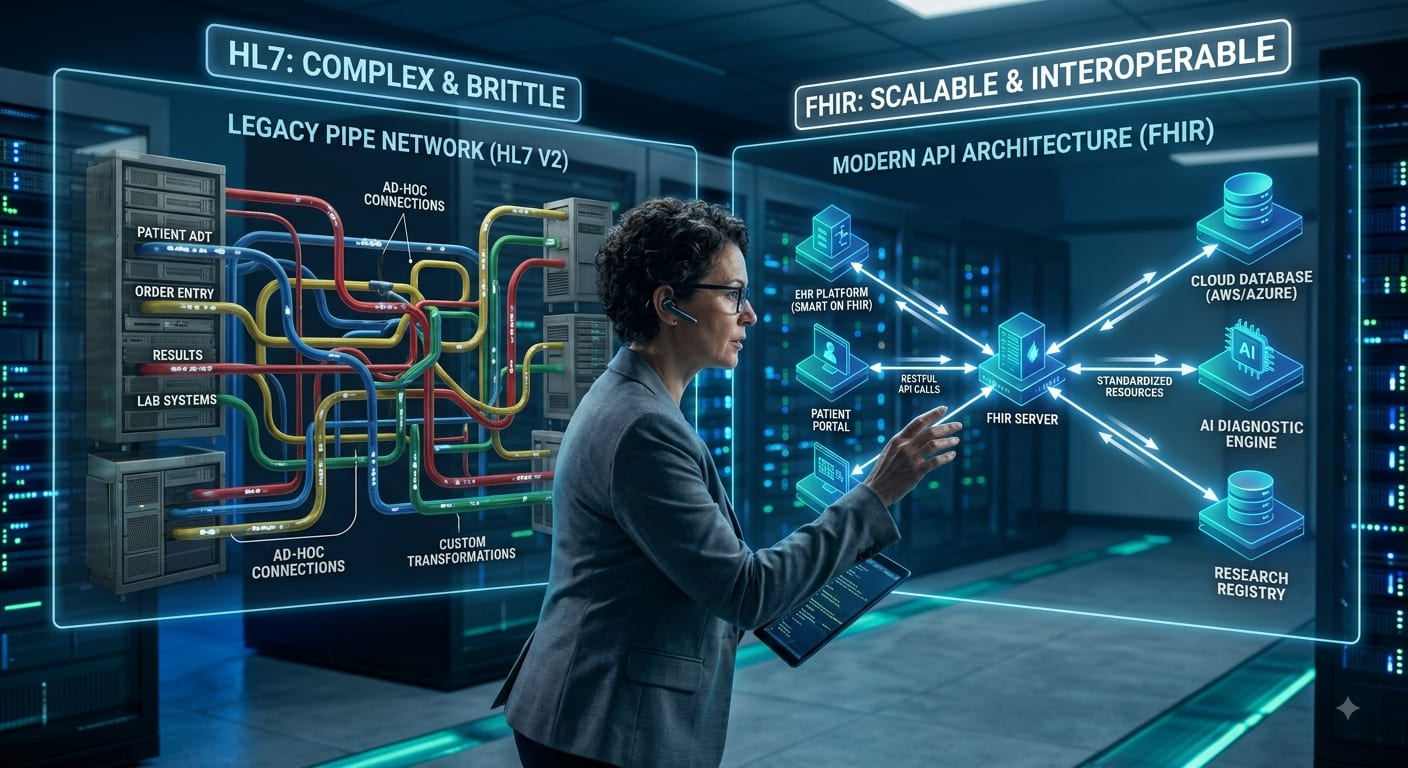
Flexibility without standardization. HL7 v2 is highly flexible, allowing implementers to use optional fields, extend messages with custom data elements, and interpret ambiguous specifications in different ways. The result is that two systems that both claim HL7 v2 compliance may not successfully exchange data without custom mapping work because each has implemented the standard differently. Healthcare integration teams frequently describe HL7 v2 integration work as a series of bilateral custom interfaces rather than a true standard.
Pipe-delimited text format. HL7 v2 messages are encoded as pipe-delimited text strings, a format that predates modern web technologies and is poorly suited for integration with contemporary web services, APIs, and cloud platforms. Consuming HL7 v2 messages in a modern application or AI system requires parsing libraries and transformation logic that add complexity and failure points to integration architectures.
Limited support for modern data concepts. HL7 v2 was designed for the clinical workflows and data concepts of the late 1980s and 1990s. It handles laboratory results, orders, and ADT events well but was not designed for the structured representation of complex clinical concepts like clinical decision support rules, genomic data, or the rich contextual data that AI systems need to function effectively.
Point-to-point interface architecture. HL7 v2 integration typically relies on point-to-point interfaces managed by integration engines such as Mirth Connect, Rhapsody, and InterSystems HealthShare. Each interface is a custom bilateral connection between two specific systems, and the total number of interfaces in a large health system can reach into the thousands. This architecture is expensive to build, difficult to maintain, and creates significant operational fragility.
HL7 v3 and CDA
HL7 also developed a version 3 specification and the Clinical Document Architecture, known as CDA, as more structured successors to HL7 v2. HL7 v3 uses XML encoding and a formal Reference Information Model to provide more rigorous data definitions. CDA documents, particularly the Consolidated CDA specification, became the standard format for clinical document exchange including discharge summaries, referral notes, and care coordination records.
HL7 v3 and CDA addressed some of the ambiguity problems of HL7 v2 but introduced significant complexity that limited adoption. The formal information model is technically rigorous but difficult to implement, and the resulting ecosystem never matched the breadth of HL7 v2 adoption. Most organizations that implemented CDA did so for specific use cases like care transitions rather than as a general-purpose integration standard.
What Is FHIR?
Fast Healthcare Interoperability Resources, universally known as FHIR and pronounced like the word fire, is the modern healthcare data interchange standard developed by HL7 International and published as a series of progressively refined specifications beginning in 2014. FHIR R4, published in 2019, is the current stable release and has become the regulatory and technical standard for healthcare interoperability in the United States.
Talk to Secure Traces
Need help applying this to your environment?
Our team can translate these ideas into a roadmap, architecture review, or pilot for your organization.
FHIR takes a fundamentally different architectural approach from HL7 v2. Rather than defining message structures for specific transaction types, FHIR defines a library of discrete data resources, each representing a specific clinical or administrative concept, and a RESTful API framework for creating, reading, updating, and deleting those resources across systems.
FHIR Resources
A FHIR resource is a structured representation of a specific healthcare concept. FHIR R4 defines over 140 resource types covering the full spectrum of clinical and administrative healthcare data. Core clinical resources include Patient, which holds patient demographic and identity information; Observation, which represents clinical measurements, laboratory results, and vital signs; Condition, which represents diagnoses and health problems; Medication and MedicationRequest, which represent medications and prescriptions; Encounter, which represents clinical visits and hospitalizations; and Practitioner, which represents healthcare providers.
Each resource has a defined structure with documented data elements, cardinality constraints, and terminology bindings that specify which code systems are used to represent coded values. This level of specification is significantly more rigorous than HL7 v2, which left many of these decisions to individual implementers.
FHIR APIs and REST Architecture
FHIR uses RESTful API patterns that are familiar to any modern software developer. Systems expose FHIR resources through HTTP endpoints using standard REST operations: GET to retrieve resources, POST to create new resources, PUT to update existing resources, and DELETE to remove resources. Resource content is encoded in JSON or XML, with JSON being the predominant format in modern implementations.
This REST API architecture means that any application capable of making HTTP requests can consume FHIR data without requiring specialized HL7 parsing libraries or integration engine software. A web application, a mobile app, an analytics platform, or an AI system can read patient data from a FHIR API using the same HTTP client libraries used for any other web service integration.
US Core Implementation Guide
The US Core Implementation Guide is a FHIR R4 specification published by HL7 that defines the minimum data elements and API behaviors required for US healthcare interoperability. US Core profiles constrain the base FHIR resources with US-specific requirements, specifying which data elements must be supported, which terminology systems must be used, and which API capabilities must be implemented.
US Core compliance is required by the CMS Interoperability and Patient Access Final Rule and the ONC 21st Century Cures Act Final Rule for most healthcare payers and providers operating in the United States. This regulatory mandate has driven broad adoption of FHIR R4 US Core across the EHR market, with Epic, Oracle Health, and virtually all other major EHR vendors now exposing patient data through FHIR R4 US Core APIs.
HL7 v2 vs FHIR R4: A Direct Comparison
Understanding where each standard excels and where each falls short requires comparing them across the dimensions that matter most for integration architecture decisions.
Data encoding format. HL7 v2 uses pipe-delimited text encoding that requires specialized parsers and is poorly suited for modern web application integration. FHIR R4 uses JSON or XML encoding that is natively supported by every modern programming language and platform without specialized tooling.
API architecture. HL7 v2 relies on point-to-point messages passing through integration engines with custom bilateral interfaces between each pair of systems. FHIR R4 uses RESTful API architecture where systems expose standardized endpoints that any authorized consumer can access without custom bilateral interface development.
Semantic precision. HL7 v2 allows significant implementer flexibility that leads to semantic inconsistency across implementations. FHIR R4 with US Core profiles provides more rigorous data definitions with specified terminology bindings that reduce but do not eliminate semantic variation between implementations.
Regulatory status. HL7 v2 has no current US regulatory mandate. FHIR R4 US Core is required by CMS and ONC regulations for most US healthcare payers and providers, driving broad adoption across the EHR market.
AI and analytics integration. HL7 v2 messages are difficult to consume in AI and analytics systems without significant transformation work. FHIR R4 JSON resources are directly consumable by AI systems, analytics platforms, and cloud data services with minimal transformation overhead.
Legacy system coverage. HL7 v2 is supported by virtually every clinical system currently deployed in US healthcare, including systems that were installed in the 1990s and early 2000s and cannot be upgraded. FHIR R4 is supported by modern EHR platforms but is not available from legacy clinical systems that have not been updated.
Transaction volume and throughput. HL7 v2 integration engines are optimized for high-volume message processing and are well-suited for real-time clinical transaction feeds like ADT events and laboratory results. FHIR R4 APIs are well-suited for query-based access patterns but require additional architectural consideration for high-volume real-time transaction scenarios.
The practical conclusion for most healthcare organizations is that HL7 v2 and FHIR R4 are not competing standards where one replaces the other. They are complementary standards that serve different integration patterns, and most mature healthcare integration architectures use both.
Why FHIR R4 Has Become the Foundation for Healthcare AI Integration
The emergence of AI in healthcare has elevated FHIR R4 from a regulatory compliance requirement to a strategic technology foundation, because FHIR is simply a far better fit for AI integration than HL7 v2.
AI systems consume structured JSON natively. Large language models, machine learning platforms, and AI orchestration frameworks are all built to work with structured data in JSON format. FHIR R4 resources are JSON objects with well-defined schemas that AI systems can parse, index, and reason over without specialized transformation layers. HL7 v2 pipe-delimited messages require transformation into a structured format before they can be consumed by AI systems, adding latency and complexity to every AI data pipeline.
FHIR enables real-time clinical data access. AI systems that support clinical decision-making need access to current patient data at the point of care, not batch-loaded extracts from overnight ETL processes. FHIR REST APIs enable real-time patient data retrieval using a single authenticated API call, giving AI systems access to current medications, diagnoses, lab results, and clinical history without requiring pre-loaded data warehouses.
Talk to Secure Traces
Need help applying this to your environment?
Our team can translate these ideas into a roadmap, architecture review, or pilot for your organization.
FHIR supports the retrieval-augmented generation architecture that healthcare AI requires. Retrieval-augmented generation, known as RAG, is the AI architecture pattern most relevant to clinical AI applications. RAG systems retrieve relevant context from authoritative data sources at inference time and provide that context to the AI model as grounding for its response. FHIR APIs are the natural retrieval layer for clinical RAG systems, providing structured, queryable access to patient data that can be retrieved, filtered, and formatted for AI model context.
FHIR provides the semantic structure that AI models can reason over. A patient medication represented as a FHIR MedicationRequest resource contains structured data elements for the medication code, dose, route, frequency, prescriber, and clinical indication, all encoded with standard terminology. An AI model presented with this structured resource can reason about the medication with clinical precision. A medication buried in a pipe-delimited HL7 v2 segment requires parsing and interpretation before an AI model can engage with it meaningfully.
FHIR US Core defines the minimum dataset for AI clinical applications. The US Core Implementation Guide defines which patient data elements must be available through FHIR APIs at any compliant EHR, providing a predictable minimum dataset that AI application developers can rely on across different health system deployments. This predictability is essential for building AI applications that work across multiple EHR environments rather than requiring custom development for each EHR vendor.
Building a Modern Healthcare Interoperability Architecture for AI
Healthcare organizations that want to deploy AI systems with access to real-time clinical data need an interoperability architecture that bridges the gap between their existing HL7 v2 integration environment and the FHIR R4 APIs that AI systems consume.
Layer 1: Legacy HL7 v2 Integration Engine
The integration engine layer handles the HL7 v2 message traffic that flows between legacy clinical systems. Integration engines like Mirth Connect, Rhapsody, and InterSystems HealthShare receive, parse, route, and transform HL7 v2 messages, maintaining the real-time clinical transaction flows that keep EHR, laboratory, pharmacy, and imaging systems synchronized.
This layer should be maintained and optimized for the high-volume, low-latency transaction patterns that HL7 v2 handles well. Replacing HL7 v2 interfaces between legacy systems with FHIR APIs is generally not practical or necessary unless the legacy systems are being replaced as part of a broader modernization initiative.
Layer 2: FHIR API Layer
The FHIR API layer exposes patient data through standardized FHIR R4 endpoints that AI systems, analytics platforms, and modern applications consume. Modern EHR platforms including Epic and Oracle Health expose native FHIR R4 APIs that can be accessed directly. For systems that do not natively expose FHIR, a FHIR facade layer built on the integration engine can transform HL7 v2 data into FHIR resources exposed through a standardized API.
Cloud-native FHIR platforms including AWS HealthLake and Azure Health Data Services provide managed FHIR server infrastructure that can aggregate data from multiple source systems and expose a unified FHIR API across the organization's clinical data estate.
Layer 3: AI Data Pipeline and RAG Platform
The AI data pipeline layer retrieves FHIR resources from the FHIR API layer, applies any necessary transformation and enrichment, and loads the data into the vector stores and retrieval indexes that power RAG-based AI applications. Patient records retrieved through FHIR APIs must be processed with PHI detection and redaction controls before they are loaded into AI training datasets or retrieval indexes.
The Secure Traces AI Solutions practice builds RAG platforms on client FHIR data as a standard component of its healthcare AI engagements, including vector store design, chunking strategy, evaluation harness, and PHI guardrails that ensure clinical data consumed by AI systems is handled within HIPAA-compliant architectural boundaries.
Layer 4: MCP Gateway for AI Agent Access
AI agents that need to access live FHIR data during inference require a governed connectivity layer that controls which agents can access which FHIR endpoints, logs all data access with an immutable audit trail, and applies PHI redaction controls before sensitive data reaches the AI model context. This is the role of the MCP gateway in a healthcare AI architecture.
Without an MCP gateway governing FHIR API access by AI agents, the organization has no reliable audit trail of what patient data each AI agent accessed, no enforcement of least-privilege access at the FHIR resource level, and no PHI guardrails preventing sensitive identifiers from appearing in AI model outputs or logs. The Secure Traces AI Solutions practice deploys MCP gateway architecture as a foundational component of every agentic AI engagement, with FHIR API access governed at the gateway layer alongside all other enterprise system connections.
FHIR Security and HIPAA Compliance Considerations
Deploying FHIR APIs in a healthcare environment creates data access capabilities that must be governed with appropriate security controls to satisfy HIPAA requirements and prevent unauthorized access to patient data.
OAuth 2.0 and SMART on FHIR authentication. FHIR APIs must be secured with robust authentication and authorization controls. The SMART on FHIR authorization framework, built on OAuth 2.0, has become the standard for FHIR API access control in healthcare. SMART on FHIR defines authorization flows for both user-facing clinical applications and backend service access, with granular scopes that restrict API access to specific resource types and patient populations.
API security monitoring. FHIR APIs that expose patient data at scale are high-value targets for attackers seeking bulk PHI access. API security monitoring should detect and alert on unusual access patterns including bulk data export requests, access from unexpected geographic locations or IP addresses, and access volumes that exceed normal clinical workflow patterns.
Audit logging for FHIR API access. Every FHIR API call that retrieves patient data must be logged with the identity of the requesting application or user, the resources accessed, the timestamp of access, and the parameters of the request. These logs must be retained and available for review to satisfy HIPAA audit control requirements.
Business Associate Agreements for FHIR platform vendors. Cloud FHIR platform vendors including AWS HealthLake and Azure Health Data Services process PHI as part of their services and must be covered under Business Associate Agreements before patient data is loaded into these platforms.
The Cybersecurity services practice at Secure Traces provides API security monitoring, SIEM integration for FHIR access logs, and HIPAA compliance support for healthcare organizations deploying FHIR infrastructure, ensuring that the expanded data access capabilities that FHIR enables are matched by appropriate security controls.
Talk to Secure Traces
Need help applying this to your environment?
Our team can translate these ideas into a roadmap, architecture review, or pilot for your organization.
Common Healthcare FHIR Integration Use Cases for AI
Understanding the specific AI integration use cases that FHIR R4 enables helps healthcare technology leaders prioritize their interoperability investments.
Clinical documentation AI copilots. AI copilots that assist clinicians with documentation need access to the patient context from the current encounter and relevant history to generate accurate, relevant documentation suggestions. FHIR APIs provide real-time access to the patient problem list, medication list, recent lab results, and encounter notes that clinical documentation AI systems use as context.
Claims processing and revenue cycle AI. Claims AI systems that validate coding accuracy against clinical documentation need to read both the clinical encounter data from the EHR and the claim data from the revenue cycle system. FHIR APIs from the EHR provide structured access to diagnosis codes, procedure codes, and clinical documentation that the claims AI uses for validation. The Secure Traces Healthcare and Pharmacy Technology practice delivers claims workflow automation built on FHIR data pipelines with 837/835 EDI integration.
Prior authorization automation. Prior authorization AI systems need to read the clinical orders requiring authorization, the relevant clinical documentation supporting medical necessity, and the patient eligibility and coverage data from the payer. FHIR APIs connect all three data sources in a format that prior authorization AI can consume without custom HL7 v2 parsing.
Care gap identification and population health. Population health AI systems that identify patients with care gaps need to query FHIR data at the population level, filtering by diagnosis, medication, lab result, or procedure code criteria. FHIR search operations support these population-level queries in ways that HL7 v2 point-to-point messaging does not.
Pharmacy and medication management AI. Pharmacy AI systems that detect drug interactions, validate dosing, or support medication reconciliation need access to structured medication data from FHIR MedicationRequest and MedicationStatement resources, along with patient diagnosis and allergy information from Condition and AllergyIntolerance resources. The Secure Traces Healthcare and Pharmacy Technology practice delivers pharmacy management and PBM integrations including eRx and NCPDP SCRIPT alongside FHIR-based clinical data pipelines.
Implementing HL7 to FHIR Migration: Practical Considerations
Many healthcare organizations operate in a hybrid state where some systems expose native FHIR APIs while others still communicate exclusively through HL7 v2. Managing this hybrid environment and migrating toward a predominantly FHIR-based integration architecture requires a structured approach.
Inventory your current integration landscape. Before planning migration, document all existing HL7 v2 interfaces, the systems they connect, the message types they carry, and the clinical workflows they support. This inventory is the foundation for migration planning and helps identify which interfaces can be replaced with FHIR APIs versus which must remain as HL7 v2 for the foreseeable future due to legacy system constraints.
Prioritize FHIR adoption for new integrations and AI use cases. Rather than migrating existing HL7 v2 interfaces wholesale, prioritize building new integrations on FHIR from the beginning and target FHIR adoption specifically for AI use cases where the benefits of FHIR over HL7 v2 are greatest. New application deployments, AI system integrations, and cloud platform connections should use FHIR R4 as the default unless there is a specific technical reason that prevents it.
Build a FHIR facade for legacy systems that cannot upgrade. For legacy clinical systems that communicate only in HL7 v2 and cannot be upgraded to support native FHIR APIs, an integration engine-based FHIR facade can transform HL7 v2 messages into FHIR resources and expose them through a FHIR API endpoint. This approach allows AI systems and modern applications to consume data from legacy systems through FHIR APIs without requiring the legacy systems themselves to be upgraded or replaced.
Validate FHIR data quality before loading into AI systems. FHIR resources retrieved from EHR APIs may contain missing data elements, non-standard code values, or semantic inconsistencies between implementations. AI systems that consume FHIR data without data quality validation may produce incorrect or misleading outputs based on incomplete or inconsistent input data. Building a data quality validation layer into the FHIR data pipeline is an essential step before FHIR data is used for AI training or inference.
The Secure Traces Healthcare and Pharmacy Technology practice delivers HL7 v2 and FHIR R4 API design, integration engine deployment, and FHIR facade development as core service capabilities, supporting healthcare organizations at every stage of their interoperability architecture modernization journey.
How Secure Traces Supports HL7 and FHIR Integration
Secure Traces delivers end-to-end HL7 and FHIR interoperability services as a core component of its Healthcare and Pharmacy Technology practice, with documented capabilities for HL7 v2.x message processing, HL7 FHIR R4 US Core API design and operation, FHIR facade development over legacy HL7 v2 feeds, and integration with leading EHR platforms including Epic and Oracle Health through Mirth Connect, Redox, and direct FHIR API connections.
The practice also delivers cloud-native FHIR data platform deployment on AWS HealthLake and Azure Health Data Services, providing healthcare organizations with managed FHIR server infrastructure that aggregates clinical data from multiple source systems and exposes a unified FHIR API for AI system consumption.
For healthcare organizations deploying AI systems on FHIR data, the AI Solutions practice delivers the RAG platform architecture, vector store deployment, PHI guardrails, and MCP gateway governance that make FHIR-powered AI deployments secure, compliant, and auditable in regulated clinical environments.
The Cybersecurity services practice provides the security monitoring, SIEM integration, and HIPAA compliance support that protect FHIR API infrastructure from unauthorized access and ensure that FHIR-enabled data access capabilities are matched by appropriate security controls and audit logging.
To learn how Secure Traces can help your organization build a modern HL7 and FHIR interoperability architecture that powers AI integration while satisfying HIPAA requirements, contact Secure Traces to schedule a consultation.
Conclusion
HL7 v2 and FHIR R4 are both essential components of the healthcare interoperability landscape in 2026, but they serve fundamentally different roles. HL7 v2 remains the dominant standard for real-time clinical transaction processing between legacy systems and will continue to operate in most healthcare environments for years to come. FHIR R4 has become the standard for modern healthcare API integration, regulatory compliance, and AI system data access, driven by CMS and ONC mandates and the broad adoption of FHIR-native APIs across the EHR market.
For healthcare organizations investing in AI, the strategic implication is clear: FHIR R4 is the interoperability foundation that makes production AI deployment possible. AI systems that need real-time access to structured patient data, the ability to query clinical data at population scale, and a format that AI reasoning engines can engage with directly require FHIR R4 APIs as their data access layer. HL7 v2 serves the transaction processing backbone that keeps clinical systems synchronized, while FHIR serves the AI and analytics layer that transforms that clinical data into actionable intelligence.
Building the bridge between these two layers, through FHIR facades over legacy HL7 v2 feeds, cloud FHIR platform deployment, and MCP gateway-governed AI agent access to FHIR APIs, is the interoperability architecture investment that positions healthcare organizations to realize the full value of AI in clinical and operational environments.
About the author
Founder & CEO, Secure Traces
30+ years in enterprise cybersecurity · Former Verint · Former GE
Natraj is the Founder and CEO of Secure Traces with over three decades of experience in enterprise cybersecurity, cloud infrastructure, and IT modernization. He has held senior security and architecture roles at Verint and GE, and advises boards on AI governance, SOC modernization, and cyber-risk strategy.